
Mpox Updates
Mpox Situation in South Africa: 1 January 2026 to date
As of 22 September 2026, a total of 22 mpox cases have been laboratory confirmed in South Africa. These cases have been reported from the Western Cape (n=18), Gauteng (n=3) and KwaZulu-Natal (n=1) provinces. Thirteen of the 18 mpox cases reported from the Western Cape province have been confirmed since mid-August 2026. Based on available information, the cases are grouped into two clusters of close contacts, with investigations ongoing. Preliminary analyses indicate that Clade Ib mpox virus is involved in both clusters, with a complete final analysis pending.
Overview
Mpox (previously named monkeypox) is a viral disease caused by infection with the monkeypox virus (also referred to as the mpox virus), a member of the genus Orthopoxvirus in the family Poxviridae. Mpox has been historically reported in several countries in West and Central Africa, attributed to being naturally harboured by animals found in this part of Africa. It is believed that rodents, most likely certain species of squirrels found in the deep-forested areas of this region, may be the natural host of the virus. These countries are deemed endemic for the virus.
Mpox virus infections in humans have historically been noted in these countries, albeit rarely. However, since the 1990s, there has been an increasing number of confirmed mpox cases in certain endemic countries. This has in part, been attributed to the discontinuation of smallpox vaccination around 1980 (different countries stopped vaccinating at different times), after smallpox was successfully eradicated. Smallpox vaccination provided cross-protection against mpox virus infection. However, over time, and following the cessation of smallpox vaccination, there has been waning immunity in the vaccinated and a growing unvaccinated population. Additionally, it may be that other factors have and are increasing the risk of zoonotic spillover of the virus, but this is not well understood yet. The recent mpox epidemics have been characterized by sustained human-to-human transmission, which has resulted in the emergence of novel variants of the virus.
Since the onset of the multi-country outbreak in May 2022, mpox has spread across multiple regions worldwide, with sustained transmission initially associated predominantly with Clade IIb mpox virus, particularly lineage B.1. In 2023, a distinct lineage, Clade Ib mpox virus, emerged in the Democratic Republic of the Congo (DRC), with evidence of sustained human-to-human transmission. From 2024 onwards, Clade Ib mpox virus spread from the DRC to neighbouring African countries and subsequently to countries outside Africa. According to the World Health Organization (WHO) Multi-country External Situation Report No. 69, published on 14 September 2026, 35 countries in Africa reported 52,424 laboratory-confirmed mpox cases and 238 deaths between 1 January 2025 and 16 August 2026, corresponding to a case-fatality ratio (CFR) of 0.5%. During the six-week period from 6 July to 16 August 2026, 11 African countries reported active mpox virus transmission, with 1,153 confirmed cases and seven deaths (CFR 0.6%). The highest numbers of confirmed cases during this period were reported in Madagascar (n=785), Angola (n=184), Kenya (n=94), the DRC (n=41), and Cameroon (n=28). Clade Ib mpox virus transmission has continued to expand geographically; by August 2026, community transmission outside Central and East Africa had been documented in several European countries, including Czechia, France, Germany, Ireland, Italy, the Netherlands, Portugal, Switzerland and the United Kingdom. WHO also reported the first detection of Clade Ib in Chile and Hungary during this period.
In 2022, at the first peak of the multi-country outbreak, a total of five laboratory-confirmed mpox cases were reported in South Africa, associated with the Clade IIb B1.7 variant. This variant was widely circulating in multiple countries at that time, as three of the five cases confirmed a history of international travel. During 2023, no laboratory-confirmed cases of mpox were reported in South Africa. This coincided with a global trend in reduction of mpox cases. Between May and October 2024, a total of 25 laboratory-confirmed mpox cases, including three deaths, were reported in South Africa. All but one case reported no travel history outside of South Africa, which implies local transmission. The Clade IIb B1.20 variant was found in all the cases without international travel history, whereas Clade IIb B1.6 was found in one case who returned from Peru before developing the illness. No cases of the Clade Ib variant were reported in South Africa in 2022 and 2024. During 2025, a total of 15 mpox cases were confirmed from Gauteng (n=8), KwaZulu-Natal (n=5), Western Cape (n=1), and North West (n=1) provinces. This included 12 Clade Ib mpox virus associated cases, and two cases linked to Clade IIb mpox virus. The clade assignment for one of the 2025 cases could not be resolved through sequencing due to limited sample.
For more information on how to prevent the disease in South Africa, click here.
Recent Updates



FAQ
Most frequently asked questions and answers about Mpox
In countries, where the natural animal host of the virus are found, the monkeypox virus may be spread from handling infected bush meat, an animal bite or scratch, body fluids and contaminated objects. The monkeypox virus has been found in many animal species: rope squirrels, tree squirrels, Gambian rats, striped mice, dormice and primates. Certain species of rodents are suspected of being the main disease carrier or host (reservoir host) of mpox, although this has not been proven yet.
In countries, where zoonotic transmission is not reported, persons are most likely to be exposed to mpox through contact with an individual that is already sick with mpox. Cases of mpox spreading through animals, outside of the endemic areas, are very rare, but may involve the exotic pet trade or potentially through contact with infected animal- derived materials such as skins and leather. Person-to-person transmission involves close contact with an infected person or materials that have been contaminated by an infected person.
In the context of the multi-country outbreak, a notable mode of transmission has been through sexual contact in the community of men having sex with men (MSM). A risk factor identified from early epidemiological investigations is having multiple sexual partners. It is also believed that several large social gatherings may have served as super-spreading events aiding in the international spread of the virus.
The incubation period (time from infection to symptoms) for mpox is on average 7−14 days but can range from 5−21 days. Initial symptoms include fever, headache, muscle aches, backache, chills and exhaustion.
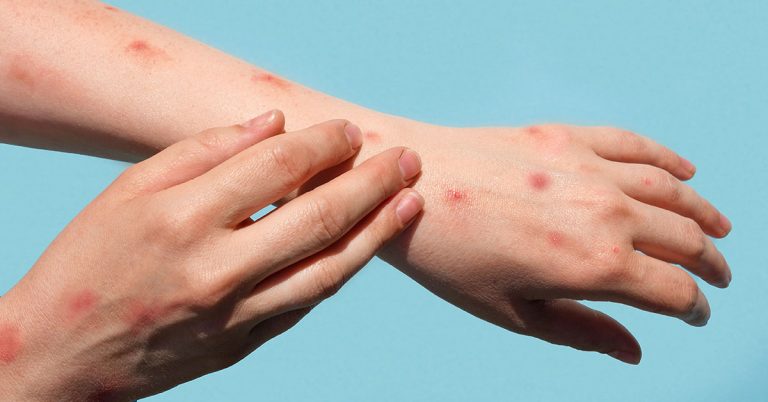
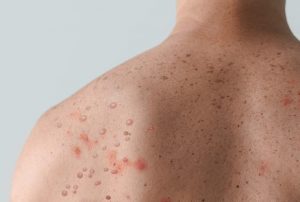
Within 1-3 days of onset of disease, blister-like lesions will develop on the face, the extremities including soles of the feet and palms of the hands. The lesions may however occur on other parts of the body. The number of lesions will vary and lesions tend to appear similar in appearance and size (i.e. will be at the same stage of development). The lesions progresses through several stages before scabbing over and resolving. Most human cases resolve within 2-4 weeks of onset without side-effects. The case fatality rate in more recent outbreaks have been on average 1%.
There are many other causes of rash illness, many of which are fairly common, that may be managed or treated in different ways. It is important to diagnose these diseases accurately in order for appropriate management to ensue.
An infected person is contagious from the onset of the rash/lesions through the scab stage. Once all scabs have fallen off, a person is no longer contagious. It is currently not known how long viable virus may persist for example in semen.
Mpox is diagnosed by a healthcare worker in consideration of the clinical presentation of the patient. The nature of the rash would be the most telling sign.
However, the healthcare worker will consider possible exposures for the case with the consideration that the likelihood of contracting mpox is very low. Many other diseases, such as chickenpox, may cause similar rashes and are more common.
Samples can be tested at the National Institute for Communicable Diseases or private pathology services (contact your preferred service for more information) to confirm a diagnosis of mpox. For more information on laboratory testing of mpox, refer to the disease index on the website.
Treatment is supportive, as with most viral infections. Most human cases of mpox do not require any specific treatment and the disease resolves on its own. There are anti-viral drugs that a clinician may consider using for treatment of more severe cases of mpox on a case-by-case basis. One such anti-viral includes tecovirimat that is used for people with severe mpox disease or those with weakened immune systems.
Tecovirimat can reduce the amount of virus in the body and may help to treat severe mpox disease involving the eyes, mouth, throat, genitals and anus. It is currently unknown whether tecovirimat works or how well it works to treat mpox. Researchers are now testing the safety and effectiveness of tecovirimat for all people with mpox.
Mpox outbreaks can be controlled by diagnosis and laboratory confirmation of cases. This allows for contact tracing and monitoring to enable the pro-active recognition of any other linked cases of mpox. It is recommended that confirmed cases of mpox isolate to ensure that risk of transmission is minimized. Isolation may be through self-isolation at home if circumstances allow, but cases may be isolated in hospital if so required.
The World Health Organization did not recommend mass vaccination as a measure to contain the outbreak. Nonetheless, the United States and certain European nations are providing smallpox vaccination to high-risk households and identified close contacts up to 14 days after exposure and gay and bisexual men with multiple sex partners.
The implications for South Africa are that the risk of importation of mpox is a reality as lessons learnt from COVID-19 have illustrated that outbreaks in another part of the world can fast become a global concern. The WHO has not recommended any travel restrictions and are working with the affected countries to limit transmission and determine sources of exposure.
South Africa reported 5 cases in 2022 and 24 cases in 2024, as of August 2024. These cases have been associated with Clade IIb, the global outbreak strain. No cases of Clade I have been detected in South Africa to date. The mpox risk classification for South Africa is moderate.
